Is Melanotan II legal?
Not approved · not compoundable- FDA status
- Melanotan II is not FDA approved. It was moved off FDA’s Category 2 safety-risk list in 2026 after its nomination was withdrawn, but it was not added to the 503A bulks list.
- Compounding
- That leaves no routine legal path for a US compounding pharmacy to prepare it.
- Prescription
- There is no approved US prescription product for Melanotan II.
- Online market
- Products sold online are labelled “for research use only”: not made, tested or labelled for human use, and often mislabelled.
US status checked October 2026 against FDA’s compounding lists. Sources at the foot of the page.
What is Melanotan II?
Melanotan II, often shortened to MT-2, is a synthetic peptide based on alpha-melanocyte-stimulating hormone, the body's natural signal for skin pigment. It was made at the University of Arizona in the late 1980s and early 1990s, in the same program that produced melanotan I. The goal was a sunless tan that might lower skin cancer risk.
Early volunteers noticed something else. Along with tanning, the peptide caused nausea, reduced appetite and spontaneous erections. That finding led to small pilot studies in men with erectile dysfunction and, eventually, to a derivative called bremelanotide. Bremelanotide was approved by the FDA in 2019 as Vyleesi for low sexual desire in premenopausal women.
Melanotan II itself was never approved anywhere. It is sold online as a research chemical and used for tanning, appetite suppression and sexual effects. Regulators in the US, UK, Australia and elsewhere have issued public warnings about it.
- Anecdotal only
- In vitro only
- Animal models only
- Preliminary human
- Clinical trials
- Regulator approved
How Melanotan II works
Your body has a family of melanocortin receptors. MC1R on skin pigment cells controls tanning. MC3R and MC4R in the brain help regulate appetite, energy use and sexual arousal. Natural alpha-MSH touches several of these. Melanotan II does the same, only much more strongly and for longer.
That is the core problem. You cannot take Melanotan II for a tan without also stimulating the brain receptors that cause nausea, appetite loss, flushing and erections. The effects come as a package.
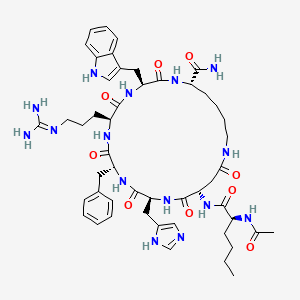
Chemically, Melanotan II is a cyclic lactam heptapeptide, Ac-Nle-cyclo[Asp-His-D-Phe-Arg-Trp-Lys]-NH2. The ring structure and the D-phenylalanine protect it from enzymes and lock it into a shape that binds melanocortin receptors with high affinity. It is a potent, non-selective agonist at MC1R, MC3R, MC4R and MC5R. MC1R signaling through cyclic AMP raises eumelanin production in melanocytes. MC4R activation in the hypothalamus and spinal pathways reduces food intake and triggers erectile responses, and it also drives the nausea and blood pressure effects.
One family of receptors controls skin pigment, appetite and sexual arousal. Drugs differ mainly in which receptor they favour: afamelanotide (MC1R), setmelanotide (MC4R), bremelanotide (MC4R), melanotan II (several).
What the research shows on Melanotan II
Human data on Melanotan II is limited to a handful of small studies from the 1990s and early 2000s. Small early trials in healthy volunteers showed that injections darkened skin, mainly in sun-exposed areas, and confirmed the nausea, yawning and stretching, and erections seen anecdotally. Small crossover studies in men with erectile dysfunction reported erections after injection compared with placebo. These studies had dozens of participants at most and lasted days to weeks.
None of that work led to approval for Melanotan II itself, although it helped map the brain's melanocortin system that later approved drugs target. The developers moved on to bremelanotide, which keeps the sexual effects but has less tanning activity, and to more selective molecules. There are no long-term trials of Melanotan II for any use, and no trials of the doses or cycles used by people who buy it online.
Much of what is known about its harms comes from case reports. These describe new or rapidly changing moles, eruptive naevi, and melanomas diagnosed in users. Case reports cannot prove cause, but they are consistent with what the drug does to pigment cells. Other reports describe priapism, kidney problems and muscle breakdown after use, although these are rare and hard to attribute.
Studied for: Tanning, Appetite suppression, Erectile function.
Melanotan II reference data
| Sequence | Ac-Nle-cyclo[Asp-His-D-Phe-Arg-Trp-Lys]-NH2 |
|---|---|
| Molecular weight | 1,024.2 Da |
| CAS number | 121062-08-6 |
| FDA status | Not approved for any indication. |
| Prohibited in sport | Not listed |
Melanotan II dosage in published research
Daily loading then 2-3x weekly maintenance · usually run for about 4 weeks. A reference pattern, not a prescription.
Open this in the dosage calculator ↗
How Melanotan II is used in practice
There is no legitimate medical use. Melanotan II is not prescribed by US telehealth services and is not a lawful compounding ingredient. It is bought online as freeze-dried powder, mixed with bacteriostatic water, and injected under the skin. Nasal sprays are also sold. Users commonly combine injections with sunbed sessions to speed tanning, which adds UV damage to the equation.
Product quality is a known issue. Laboratory analyses of products bought online have found impurities and peptide content that does not match the label, and sterility is never guaranteed. Tanning products sold through social media and gyms often give no clear manufacturer. Because there is no oversight, a buyer has no reliable way to know what is in the vial. Social media has driven much of the recent interest. Tanning injections and nasal sprays are promoted with before-and-after photos, often with no mention of side effects or of who made the product. Health agencies in several countries have responded with public warnings aimed at young adults and sunbed users.
Melanotan II risks and side effects
Side effects are common and appear early. They include nausea, often severe with the first doses, facial flushing, spontaneous erections, yawning, fatigue, reduced appetite and darkening of the face and moles. Some people develop new freckles or patches of uneven pigment.
The most serious concern is skin cancer. Melanotan II darkens existing moles and can make new ones appear, which makes changes harder to spot. People with a personal or family history of melanoma, or with many atypical moles, face the highest stakes. Anyone who has used it should have moles checked by a dermatologist.
Other risks include priapism, which is a medical emergency, raised blood pressure and heart rate, and possible interaction with erectile dysfunction drugs. It should not be used in pregnancy or by people with heart disease. Injecting unregulated powders carries a risk of infection and abscesses. Long-term safety is simply unknown.
Reported side effects
Alternatives to Melanotan II
For a tan, sunless tanning lotions and sprays with dihydroxyacetone give color without injections or UV exposure. Sun protection is still needed.
For sexual function, approved options have real evidence. PDE5 inhibitors such as sildenafil and tadalafil treat erectile dysfunction. Bremelanotide (Vyleesi) and flibanserin (Addyi) are approved for low sexual desire in premenopausal women. For appetite and weight, GLP-1 based drugs such as semaglutide and tirzepatide are far better studied, and setmelanotide (Imcivree) is an approved MC4R agonist for specific genetic forms of obesity.
The bottom line on Melanotan II
Melanotan II reliably tans the skin, but it cannot do so without nausea, sexual effects and darkening of moles, and it has never been approved anywhere. It is sold only through an unregulated market with real quality problems. Safer tanning methods and approved drugs for each of its side uses already exist.
Questions for a clinician
- What evidence applies to my situation, and at what level?
- What established alternatives should I consider first?
- What monitoring would be necessary, and how often?
- Can this be prescribed at all where I live, or only sold for research?
Melanotan II FAQ
What is Melanotan II?
A non-selective melanocortin agonist that causes tanning, appetite suppression and erections. Subject of repeated regulatory warnings. It is classed as melanocortins.
Is Melanotan II FDA approved?
No. Melanotan II is not approved by the FDA for any indication. Material sold online is labelled for research use only.
Is Melanotan II legal in the US?
Melanotan II is not FDA approved. It was moved off FDA’s Category 2 safety-risk list in 2026 after its nomination was withdrawn, but it was not added to the 503A bulks list. That leaves no routine legal path for a US compounding pharmacy to prepare it.
What dose of Melanotan II is used in research?
Published research and practitioner protocols report 250 mcg - 1 mg, daily loading then 2-3x weekly maintenance, typically for 4 weeks. This is a reference range, not a recommendation; dosing should be set by a licensed clinician.
How is Melanotan II reconstituted?
A 10 mg vial mixed with 2 mL of bacteriostatic water gives 5.0 mg/mL. At that concentration 250 mcg is 5.0 units on a 100-unit insulin syringe.
What are the side effects of Melanotan II?
Reported side effects include nausea, facial flushing, spontaneous erections, darkening of moles, appetite loss, lethargy. Contraindications: melanoma history, atypical or numerous naevi, pregnancy, cardiovascular disease.
What is the half-life of Melanotan II?
The reported half-life of Melanotan II is ~1-2 hours.
Is Melanotan II banned in sport?
Melanotan II is not specifically named on the WADA prohibited list, but athletes should check the current list and their federation's rules.
References
Regulatory and primary sources
- FDA: Bulk drug substances that may present significant safety risks (Category 2 and withdrawn nominations) ↗ · content current as of April 22, 2026; checked October 18, 2026
- FDA: Bulk drug substances used in compounding under section 503A ↗ · how the 503A categories work
- PubChem compound record (CID 92432) ↗ · structure, identifiers, synonyms
- FDA: Unapproved drugs and "research use only" products ↗ · regulatory status of non-approved products
- CAS Registry Number 121062-08-6 ↗ · chemical identity
Published literature
- Falsification of biotechnology drugs: current dangers and/or future disasters?.J Pharm Biomed Anal 2018.PubMed 30165334 · doi:10.1016/j.jpba.2018.08.037
- Melanocortin peptide therapeutics: historical milestones, clinical studies and commercialization.Peptides 2006.PubMed 16412534 · doi:10.1016/j.peptides.2005.01.029
- Sympathetic and sensory innervation of brown adipose tissue.Int J Obes (Lond) 2010.PubMed 20935665 · doi:10.1038/ijo.2010.182
- Melanocortin receptor agonists, penile erection, and sexual motivation: human studies with Melanotan II.Int J Impot Res 2000.PubMed 11035391 · doi:10.1038/sj.ijir.3900582
- Melanotan II: a possible cause of renal infarction: review of the literature and case report.CEN Case Rep 2020.PubMed 31953620 · doi:10.1007/s13730-020-00447-z
- Central nervous system agents in the treatment of erectile dysfunction: how do they work?.Curr Urol Rep 2001.PubMed 12084236 · doi:10.1007/s11934-001-0044-6
- Evaluation of melanotan-II, a superpotent cyclic melanotropic peptide in a pilot phase-I clinical study.Life Sci 1996.PubMed 8637402 · doi:10.1016/0024-3205(96)00160-9
- Discovery that a melanocortin regulates sexual functions in male and female humans.Peptides 2005.PubMed 15996790 · doi:10.1016/j.peptides.2005.01.023
Literature retrieved from PubMed on October 18, 2026, favouring human studies and reviews. Numbered markers in the text show which paper supports which statement; uncited entries are background reading.